Overview
Cardiac ablation is a treatment for some irregular heartbeats, called arrhythmias (uh-RITH-me-uhs). It uses energy to treat small areas of heart tissue involved in starting or maintaining the irregular heart rhythm. The treated areas, called lesions, interrupt faulty heart signals. This can help your heart beat in a steadier rhythm.
Cardiac ablation may use heat, extreme cold or short, high-energy electrical pulses. Radiofrequency ablation uses controlled heat. Cryoablation uses extreme cold. Pulsed field ablation (PFA) uses short, high-energy electrical pulses to disrupt cell membranes through a process called electroporation. Unlike radiofrequency ablation or cryoablation, PFA doesn't use heat or cold.
Cardiac ablation most often is done with catheters. During catheter ablation, thin, flexible tubes called catheters are passed through a blood vessel to the heart. Catheter ablation doesn't require open-heart surgery. In some situations, a doctor may perform ablation during open-heart surgery.
Cardiac ablation care at Mayo Clinic
Cardiac ablation
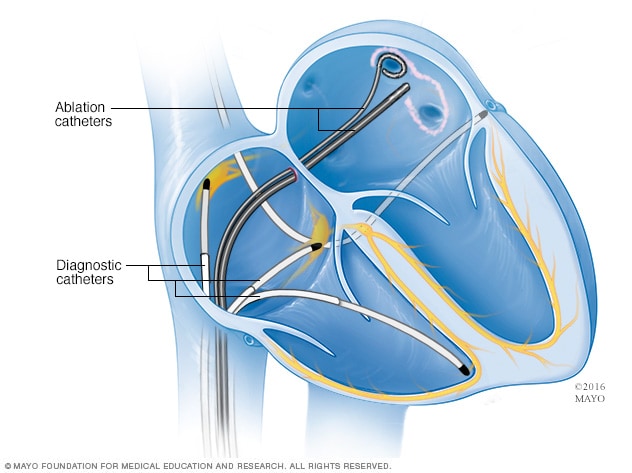
Cardiac ablation
Cardiac ablation is a treatment for irregular heart rhythms, called arrhythmias. It uses thin, flexible tubes called catheters and heat or cold energy to make tiny scars in the heart. The scars block the faulty signals that cause irregular heartbeats. This illustration shows a type of cardiac ablation called pulmonary vein isolation.
Products & Services
Types
Cardiac ablation types include:
- Atrial fibrillation ablation. Catheter ablation for atrial fibrillation uses energy to treat heart tissue involved in the irregular rhythm. This blocks faulty electrical signals that cause atrial fibrillation.
- Atrial flutter ablation. This treatment blocks the faulty electrical signals in an upper chamber of the heart. The heart's upper chambers are called the atria.
- AV node ablation. This treatment targets the atrioventricular (AV) node. The AV node carries electrical signals from the heart's upper chambers, called the atria, to the lower chambers, called the ventricles. Anyone who has this procedure needs a permanent pacemaker.
- Pulmonary vein isolation. This treatment uses energy to create small treated areas that block faulty signals. It is done in the upper left heart chamber, called the left atrium, where the four pulmonary veins connect. The pulmonary veins carry oxygen-rich blood from the lungs to the heart. Pulmonary vein isolation is used to treat atrial fibrillation.
- SVT ablation. Supraventricular tachycardia (SVT) ablation blocks faulty electrical signals that cause SVT. This can help restore a regular heartbeat.
- Ventricular tachycardia ablation. This treatment targets tissue involved in starting or maintaining ventricular tachycardia. It blocks faulty electrical signals that cause the heart's lower chambers, called the ventricles, to beat too quickly.
Why it's done
Cardiac ablation is a treatment to stop, prevent or reduce irregular heartbeats, called arrhythmias.
An arrhythmia happens when the electrical signals that tell the heart to beat don't work as they should. The heart may beat too fast or too slow. Or the pattern of the heartbeat may not be regular.
Depending on the type of irregular heartbeat, cardiac ablation may be one of the first treatments offered. Whether ablation is recommended depends on your symptoms, other heart conditions, how likely it is to control the rhythm and the risks of the ablation.
You might need cardiac ablation if:
- Medicines don't work well to control the irregular heartbeat.
- Medicines can't be used or cause side effects that are hard to manage.
- You have a rhythm that raises the risk of sudden cardiac arrest or other heart complications.
Cardiac ablation may be used to treat:
- Atrial fibrillation. Atrial fibrillation ablation may be used when symptoms continue despite medicines or other treatments, or when medicines can't be used.
- Atrial flutter. Atrial flutter ablation may be used to control symptoms or when atrial flutter keeps returning. For atrial flutter, ablation blocks faulty electrical signals in the heart's upper chambers, called the atria.
- Supraventricular tachycardia, including rhythms related to Wolff-Parkinson-White syndrome. Ablation may target an extra electrical pathway or part of an electrical circuit that lets signals travel in a loop. This blocks the faulty electrical signals that cause SVT.
- Ventricular tachycardia. For some types of ventricular tachycardia, cardiac ablation may be used when medicines or an implanted device don't control the rhythm. Ventricular tachycardia that lasts can be life-threatening and may lead to sudden cardiac arrest.
- Premature ventricular contractions (PVCs). Ablation may be used when frequent PVCs continue despite lifestyle changes and medicines. It also may be considered when PVCs cause serious symptoms or weaken the heart.
Your care team works with you to choose a treatment that fits your situation.
Risks
Cardiac ablation is an invasive procedure. This means tools enter the body through a puncture in the skin. Serious risks aren't common, but they can happen. The risks and benefits of cardiac ablation depend on:
- The ablation method and energy source.
- The heart rhythm being treated.
- Your heart health and overall health.
Possible risks include:
- Bleeding or infection at the catheter entry site.
- Damage to blood vessels or heart valves.
- A hole in the heart wall that causes blood to collect around the heart. This is called cardiac tamponade.
- A new irregular heartbeat or one that gets worse.
- A slow heart rate that may require a pacemaker.
- Blood clots or stroke. A heart attack also can happen, but it's rare.
- Death can happen, though it is very rare.
Some risks depend on the ablation method. Risks linked more closely to some methods that use heat or extreme cold include:
- Injury to the phrenic nerve, which controls the diaphragm and helps with breathing. This can happen with some balloon-based atrial fibrillation ablations.
- Narrowing of the pulmonary veins after pulmonary vein isolation or atrial fibrillation ablation. This condition is called pulmonary vein stenosis.
- Rare injury to the esophagus during some atrial fibrillation ablations that use cold or heat. The esophagus is the tube that carries food from the mouth to the stomach.
During and after the procedure, your care team checks your heart rhythm, blood pressure and catheter entry site. This helps your team find and treat any complications quickly.
Talk with your healthcare team about the risks and benefits of cardiac ablation for your specific rhythm and procedure. The team can help you learn whether cardiac ablation is right for you.
How you prepare
Before cardiac ablation, you may have tests of your heart rhythm, heart structure and overall health. The results help the heart rhythm care team plan the procedure.
Your care team may tell you that you need to stop eating and drinking the night before your treatment. Your care team also tells you if you need to take, stop or change any medicines before cardiac ablation. Don't stop taking a blood thinner unless your care team tells you to. For atrial fibrillation ablation, the procedure often is done while blood-thinning medicine is continued or paused only briefly.
Plan for someone to drive you home and help you during the early recovery period.
What you can expect
Before the procedure
Cardiac ablation usually takes place in a special room called an electrophysiology lab, often in a hospital. A healthcare professional places an IV in a vein, often in the hand or forearm. Fluids and medicines to help you relax, called sedatives, flow through the IV.
The type and amount of sedation you need depends on the rhythm, the procedure, the medical center's available options and your overall health. You may be lightly or deeply sedated. Some people get general anesthesia, which puts them in a sleeplike state.
During the procedure
During cardiac ablation, a doctor who is a heart rhythm specialist, called an electrophysiologist, places one or more thin, flexible catheters into a blood vessel and guides them to the heart. The catheters usually enter through a blood vessel in the groin. A blood vessel in the upper chest or neck area may be used for some procedures.
Tiny sensors at the catheter tips, called electrodes, record electrical signals in the heart. Your doctor and care team use this information to understand the rhythm and find the areas to treat. This important step is called an electrophysiology (EP) study. It's like making a map of the heart's electrical system.
Next, your doctor uses an ablation method suited to the rhythm.
- Radiofrequency ablation uses controlled heat to treat heart tissue.
- Cryoablation uses extreme cold to freeze heart tissue. A balloon may be inflated near the pulmonary veins to isolate them during atrial fibrillation ablation. This is called cryoballoon ablation.
- Pulsed field ablation uses short, high-energy electrical pulses. It's generally used to perform pulmonary vein isolation during atrial fibrillation ablation. Researchers continue to study other uses.
The treated areas interrupt faulty electrical signals so the signals can't start or maintain an irregular heartbeat.
For atrial fibrillation ablation, studies have found broadly similar results in rhythm-control results among radiofrequency ablation, cryoablation and pulsed field ablation.
Sedation or anesthesia can help reduce pain and anxiety. You may feel pressure or discomfort during parts of the procedure. Tell your care team if you have severe pain, shortness of breath or another symptom that concerns you.
Cardiac ablation often takes about 3 to 6 hours, though some procedures may be shorter or longer. The length depends on the rhythm being treated, the number of areas treated, the mapping needed and the ablation method.
Catheter insertion points for cardiac ablation
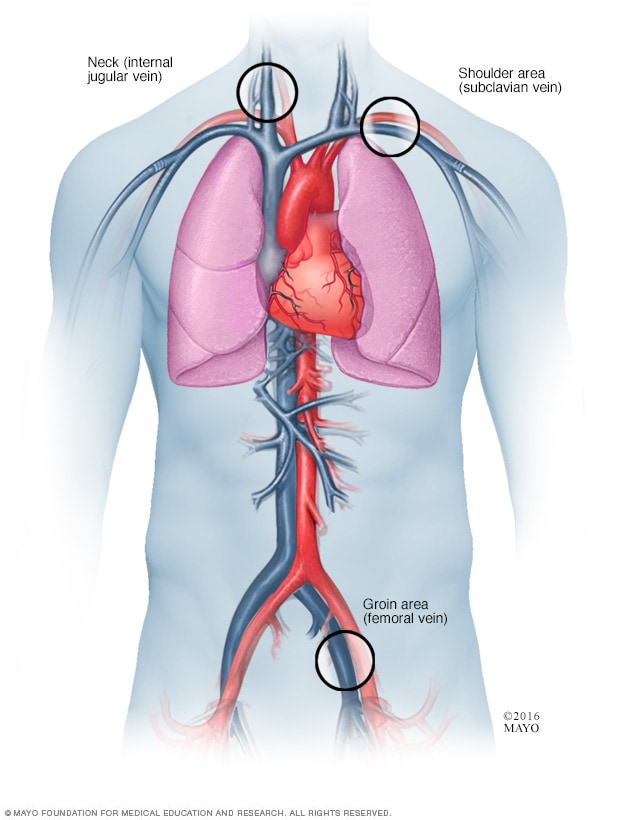
Catheter insertion points for cardiac ablation
During cardiac ablation, a doctor puts a thin, flexible tube called a catheter into a blood vessel and guides it to the heart. More than one catheter is often used. The catheter may be placed in the groin, the shoulder or the neck.
After the procedure
After your procedure, you rest in a recovery area for a few hours. A care team member checks your heart rhythm, blood pressure and catheter entry site. You may go home the same day. Some people stay overnight. Whether you go home the same day or stay overnight depends on the procedure and recovery period. Ask your healthcare team how long you will need to stay in the hospital. Also, plan to have someone drive you home.
You may feel a little sore or have some bruising or swelling at the catheter entry site as you recover after the procedure. The soreness often improves within a week. Most people can go back to their daily activities within a few days. Do not lift anything heavy for about a week. Follow your care team's instructions.
During the first eight weeks after atrial fibrillation ablation, irregular rhythms may happen and may stop over time. An early episode may not mean the ablation failed.
Your healthcare team tells you how to care for the catheter entry site. Call 911 or get emergency medical help right away if bleeding does not slow down when you put pressure on it. Follow your care team's instructions for when you return home and watch for any other warning signs, such as severe chest pain, trouble breathing or signs of a stroke.
Ask your care team when it is safe to drive, fly, travel, take a bath or drink alcohol. For atrial fibrillation, drinking less alcohol may help lower the chance of the irregular rhythm returning.
At follow-up appointments, your care team may monitor your heart rhythm and review your medicines. Irregular rhythms can come back soon after ablation or later, sometimes without clear symptoms. After cardiac ablation, contact your care team if fatigue or other symptoms are severe, get worse or last longer than expected.
Results
After cardiac ablation, an irregular heartbeat may return. Results depend on the heart rhythm that was treated, other heart conditions, the ablation method, and whether this is the first or a repeat procedure. Studies define success and monitor heart rhythm in different ways. So it's not always easy to compare results.
For atrial fibrillation, cardiac ablation can reduce how often atrial fibrillation happens and how long episodes last. It also can ease symptoms and improve quality of life compared with medicine treatment. If atrial fibrillation returns, you may need ablation again or other treatment.
After atrial fibrillation ablation, you need to take blood thinners for at least three months. How long you need to take blood-thinning medicines after that depends on your risk of stroke. Some people also may take antiarrhythmic medicine for a short time to reduce early rhythm episodes. Don't stop taking a blood thinner or other medicine unless your care team tells you to.
Success rates vary by the type of atrial fibrillation. Rates also depend on how the rhythm is monitored, how long follow-up lasts and how a study defines recurrence.
In clinical trials, atrial fibrillation returned after a first ablation in about 30% to 40% of people. The rate varies with the type of atrial fibrillation, the monitoring method and the length of follow-up.
For premature ventricular contractions (PVCs), ablation results depend on where the extra beats start and the heart's structure. Results also depend on the mapping method and whether this is the first or a repeat treatment.
Cardiac ablation hasn't been shown to increase life expectancy for everyone who has the procedure. In selected groups with atrial fibrillation and heart failure, a 2026 review of randomized trials found a lower risk of death with ablation plus medicines recommended in guidelines compared with medicines alone. These findings may not apply to everyone with atrial fibrillation or heart failure or to other types of cardiac ablation.
Clinical trials
Explore Mayo Clinic studies of tests and procedures to help prevent, detect, treat or manage conditions.
Sept. 12, 2026