Diagnosis
Diagnosing chondrosarcoma usually involves a physical exam and imaging tests. It may involve a biopsy. Cartilage tumors can be difficult to classify, so diagnosis is based on the combined findings from imaging and tissue samples.
Imaging tests
Imaging tests may include:
- X-ray. An X-ray is often the first imaging test used for a painful or swollen area of bone. Chondrosarcoma may have a characteristic pattern of mineralized cartilage on X-rays.
- MRI. An MRI gives detailed information about the size of a tumor and how far it extends through bone and nearby soft tissues.
- CT scan. A CT scan can show mineral buildup in the cartilagelike material of the tumor and changes in the bone.
Imaging can help your care team tell the difference between chondrosarcoma and noncancerous cartilage tumors, such as enchondroma and osteochondroma. However, some low-grade cartilage tumors are hard to classify by imaging alone.
For higher grade chondrosarcoma, your healthcare professional may use imaging to see if the cancer has spread to your lungs.
Biopsy
A biopsy is a procedure to remove a sample of tissue for testing in a lab. A biopsy may be needed to confirm the diagnosis and determine the tumor grade.
A biopsy is often done by an interventional radiologist or orthopedic surgeon.
Different areas within the same tumor can have different grades. For that reason, a small biopsy sample may not always include the part of the tumor that has the highest grade. Your care team looks at biopsy results together with the imaging findings.
Grades
Grade is based on [or describes] how cancer cells look under a microscope. It helps show how aggressive the cancer is likely to be. For conventional chondrosarcoma, grade is one of the most important indicators of the chance that the tumor will grow, recur or spread.
A pathologist assigns the grade by looking at how many tumor cells are present, how unusual the cells look, how actively the cells are dividing and other traits. Conventional chondrosarcoma generally is described as grade 1, grade 2 or grade 3.
- Grade 1. These tumors are the least aggressive. Many in the long bones are called atypical cartilaginous tumors (ACTs). These tumors can grow in the area where they start but are very unlikely to spread elsewhere.
- Grade 2. These tumors have a greater chance of recurrence or spreading than grade 1 tumors.
- Grade 3. These tumors are the most aggressive and have a greater chance of spreading to other parts of the body.
Not every chondrosarcoma is graded this way. For example, periosteal chondrosarcoma is not graded using the conventional framework.
More Information
Treatment
Thighbone replacement
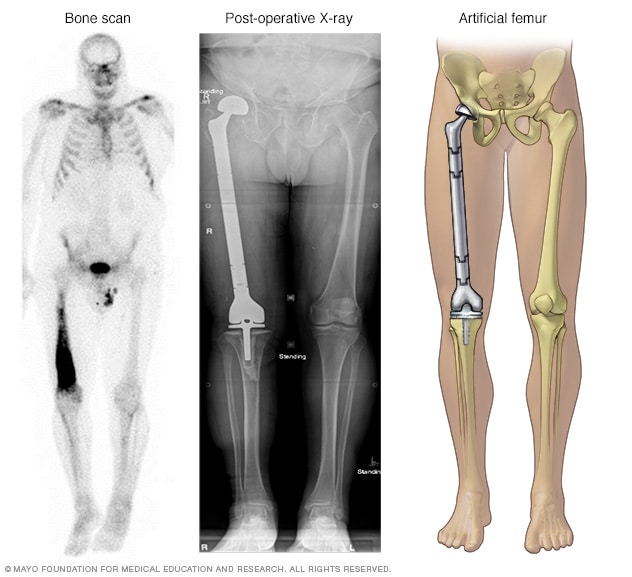
Thighbone replacement
A bone scan (left) shows cancer in right thighbone, also called the femur. The entire thighbone, the hip joint and the knee joint were replaced with artificial components.
Treatment for chondrosarcoma depends on the type, grade, location and extent of the tumor. Your care team also considers whether it can be completely removed. A sarcoma team that includes specialists in areas such as orthopedic surgery, radiation oncology and medical oncology often plans your care.
For most chondrosarcomas that haven't spread, surgery is the main treatment. It offers the best chance of cure when the tumor can be completely removed.
Surgery
The type of surgery depends on the grade and location of the tumor. Some atypical cartilaginous tumors or other low-grade lesions in an arm or leg may be treated by curettage. In curettage, a surgeon scrapes cancer cells from the bone.
Higher grade tumors and tumors in parts of the body where recurrence would be very serious generally require wider surgery. The goal is to remove the tumor along with some tissue around it that has no cancer cells. This is called a negative surgical margin.
When a tumor affects an arm or a leg, surgeons try to preserve the limb when they can remove the cancer safely. If part of a bone or joint must be removed, you may need surgery to reconstruct the limb. How the surgery affects your ability to move and use the limb depends on the tumor's location and the amount of tissue that must be removed. Your surgical team can discuss the type of surgery that is right for your tumor.
Chemotherapy
Chemotherapy has a much smaller role in chondrosarcoma treatment than it does in treatment of some other bone cancers. Standard chemotherapy usually isn't helpful for conventional chondrosarcoma, so routine chemotherapy is not used for most localized conventional tumors.
Chemotherapy may be used to treat some more aggressive types, such as mesenchymal or dedifferentiated chondrosarcoma. The evidence about the use of chemotherapy for dedifferentiated chondrosarcoma is limited and mixed, so your care team looks at potential benefits and side effects for you.
Radiation therapy
Radiation therapy uses high-energy beams to damage cancer cells. Radiation doesn't help everyone, but it can be useful in some situations.
Radiation may be considered when a tumor cannot be completely removed or when surgery is not possible. It might also be used when the tumor is in a place where more treatment close to the tumor site is needed. Proton therapy may be used for some chondrosarcomas.
Radiation side effects depend on the area treated and can appear years after treatment. Talk with your radiation therapy team about what short-term and long-term side effects to expect.
Clinical trials may be an option for some people with cancer that can't be removed by surgery, cancer that recurs or cancer that has spread, especially when there are few treatments. Your care team can tell you if clinical trials are an option for you.
More Information
Clinical trials
Explore Mayo Clinic studies testing new treatments, interventions and tests as a means to prevent, detect, treat or manage this condition.
Prognosis
Prognosis varies greatly by chondrosarcoma type, grade, location and whether the cancer has spread. Rare aggressive types can have a less favorable outlook.
Chondrosarcoma in the pelvis or other central body areas generally has a less favorable outlook than chondrosarcoma in the arms or legs. Some lower grade tumors of the skull base and cervical spine treated with surgery and proton therapy have shown high long-term survival.
It's important to keep in mind that statistics apply to large groups of people, rather than to individuals. Your care team can explain how your treatment plan may affect your individual outlook.
More Information
Coping and support
A cancer diagnosis can bring emotional and physical changes. People cope with these changes in different ways. But when you're first diagnosed with cancer, it can be hard to know what to do next.
Here are some ideas to help you cope:
- Learn enough about cancer to make decisions about your care. Ask your care team about your cancer, including your treatment options and, if you like, your prognosis. As you learn more about cancer, you may become more confident in making treatment decisions.
- Stay connected with people you care about. Keeping your close relationships strong may help you deal with your cancer. People you trust may be able to provide practical support, such as helping take care of your home if you're in the hospital. And they can serve as emotional support when you feel overwhelmed by cancer.
- Find someone to talk with. Find someone who will listen as you talk about your hopes and fears. This may be a friend or family member. The concern and understanding of a counselor, medical social worker, clergy member or cancer support group also may be helpful.
Preparing for your appointment
Preparing for your appointment can help you get the most out of the time you have with your care team. Making a list of questions can help you prepare for your visit, remember what you want to ask and take part in decisions about your care.
What you can do
- Write down your symptoms, including when they started and whether they have changed.
- Bring a list of medicines, vitamins and supplements you take, including the doses.
- Gather information about previous bone tumors, cancers, biopsies, imaging tests or treatments.
- Tell the care team if you have Ollier disease, Maffucci syndrome, hereditary multiple osteochondromas or another condition involving cartilage or bone tumors.
- Consider bringing someone you trust to help listen and take notes.
- Write down your questions and list the most important ones first.
Questions you may want to ask include:
- What type and grade of chondrosarcoma do I have?
- Has the cancer spread?
- Do I need any more imaging tests?
- What are my treatment options?
- Can surgery remove all of the cancer?
- What type of surgery do you recommend, and how might it affect how I move?
- Is chemotherapy likely to help my type of chondrosarcoma?
- Is radiation therapy an option for me?
- Are there clinical trials that may be appropriate for me?
- What is the chance that the cancer could come back?
- What do my grade, stage and tumor location mean for my outlook?
- How often will I need follow-up visits and imaging after treatment?
What to expect from your care team
Your healthcare professional may ask questions such as:
- When did you first notice pain, swelling or a lump?
- Have your symptoms been getting worse?
- Is the pain worse at night?
- Have you had weakness, numbness, or changes in how your bowel or bladder works?
- Have you ever had a cartilage tumor, bone tumor or cancer before?
- Have you ever had surgery or a biopsy in the affected area?
- Do you have Ollier disease, Maffucci syndrome or hereditary multiple osteochondromas?
- Does anyone in your family have a condition that causes many bone or cartilage growths?
Sept. 23, 2026