Diagnósticos
To diagnose heart failure with reduced ejection fraction (HFrEF), your healthcare professional examines you and asks questions about your symptoms and medical history. Your health professional checks to see if you have risk factors for heart failure, such as high blood pressure, coronary artery disease or diabetes.
Your health professional listens to your lungs and heart with a device called a stethoscope. A whooshing sound called a murmur may be heard when listening to your heart. Your health professional may look at the veins in your neck and check for swelling in your legs and belly.
Tests may be done to diagnose HFrEF and look for causes of heart failure.
Electrocardiogram (ECG or EKG)
This quick and painless test often can be done at your first healthcare appointment. An ECG records the movement of electrical signals in the heart. It can show how the heart is beating. It also can show an irregular heartbeat or signs that the heart muscle is thick. The results help your healthcare professional look for causes of heart failure. But an ECG does not diagnose HFrEF by itself.
For the ECG test, sticky patches with sensors on them go on your chest and sometimes your arms and legs. Wires connect the sensors to a computer, which prints or shows the results.
Blood tests
Blood tests can help find conditions that affect the heart or that may lead to heart failure.
- N-terminal pro-B-type natriuretic peptide (NT-proBNP). The heart releases this substance into the bloodstream when it's under increased strain or pressure. High levels may be a sign of heart failure. If NT-proBNP testing is not available, you may have a regular BNP test.
- Troponin. Troponin is a protein found in heart muscle. Higher levels of the protein may mean you have heart damage. Higher levels also may help point to conditions linked with HFrEF, such as cardiac amyloidosis.
- Estimated glomerular filtration rate (eGFR). This blood test shows how well the kidneys are working. It checks the level of a waste product called creatinine, which is made by muscles. Then the test estimates how much blood the kidneys filter each minute. In heart failure, the eGFR may go down if the kidneys are not doing their job well.
- Other blood tests. Other blood tests may be done to check for conditions that can cause heart failure. Blood tests also can tell how well other parts of the body are working, such as the thyroid, liver and kidneys.
Imaging tests
Imaging tests for heart failure with reduced ejection fraction (HFrEF) make pictures of the heart.
- Echocardiogram. Sound waves create images of the beating heart. This test shows the size and structure of the heart and heart valves and blood flow through the heart. An echocardiogram also can show how well the heart relaxes and fills with blood. The echocardiogram results say how much blood leaves your heart each time it squeezes. This is called the ejection fraction. In HFrEF, the ejection fraction is often 40% or lower. But newer guidelines move away from a specific cutoff.
- Chest X-ray. X-ray images can show the condition of the lungs and heart. The images can show whether the heart is larger than usual. They also can show fluid buildup in the lungs or other conditions that may be causing your symptoms.
- CT scan of the heart. Also called a cardiac CT scan, this test uses X-rays to create cross-sectional images of the heart. It may help look for coronary artery disease or other heart conditions that may be causing heart failure.
- Heart MRI scan, also called a cardiac MRI. This test uses radio waves and a strong magnetic field to make clear pictures of the heart tissue. It shows the structure of the heart. It also can help find heart muscle damage or conditions that may be causing heart failure.
Ecocardiograma
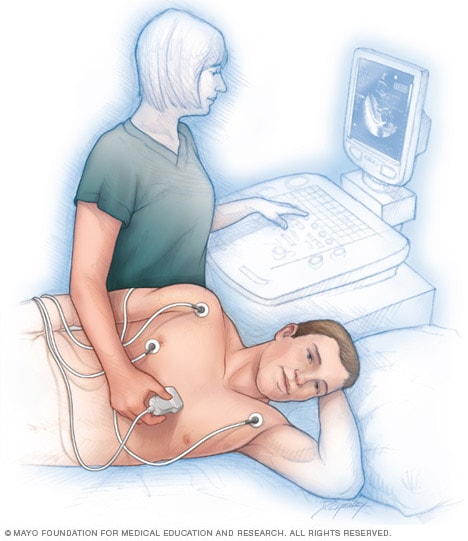
Ecocardiograma
Un ecocardiograma usa ondas sonoras para ver cómo fluye la sangre por el corazón y las válvulas cardíacas. Se colocan sensores en el pecho y a veces en las piernas que controlan el ritmo cardíaco durante la prueba. La prueba puede ayudar al profesional de atención médica a diagnosticar afecciones cardíacas.
Exercise stress testing
Exercise makes the heart pump harder and faster. An exercise stress test can show changes with blood flow within the heart. It may be used to confirm or rule out heart failure with reduced ejection fraction (HFrEF). Some people with HFrEF have changes that only show up during exercise.
These tests often involve walking on a treadmill or riding a stationary bike. A healthcare professional watches your heartbeat, blood pressure and breathing during the test.
Exercise tests can show how the heart responds to physical activity. If you can't exercise, you might get medicines that affect the heart like exercise does. An exercise stress test may be done during an echocardiogram.
Other tests
Other tests may be needed to find conditions that may lead to heart failure. They may include:
- Coronary angiogram. This test helps spot blockages in the heart arteries. The doctor places a thin, soft tube called a catheter into a blood vessel, usually in the groin or wrist. A coronary angiogram is done during a heart procedure called cardiac catheterization. For HFrEF, this test may be done if your healthcare professional thinks you may have coronary artery disease and other tests do not give a clear answer.
- Right heart catheterization. This test checks the pressures inside different heart chambers. The measurements may be taken while you are resting and during exercise. During the test, the doctor places a thin, soft tube called a catheter into a blood vessel and guides it to the right side of the heart.
- Heart biopsy. A heart biopsy is the removal of a small piece of heart tissue to be checked under a microscope. A heart biopsy can be done during cardiac catheterization. This test may help diagnose some types of heart muscle diseases that cause heart failure. Examples are myocarditis and cardiac amyloidosis. It is not routinely done to diagnose heart failure.
Más información
Tratamientos
Treatment of heart failure with reduced ejection fraction (HFrEF), also called systolic heart failure, may depend on the cause. Treatment often includes lifestyle changes and medicines. You also may need oxygen if the oxygen level in your blood is too low. If another health condition is causing the heart to fail, treating it may improve heart failure.
Some people with HFrEF need surgery to open blocked arteries or other procedures to place a device to help the heart work better.
HFrEF may improve with treatment. In some people, heart failure may go into remission. This means the condition has improved, but it does not always mean HFrEF is fully reversed.
Lifestyle changes
Lifestyle changes are an important part of heart failure with reduced ejection fraction (HFrEF) treatment. They can help you feel better, stay active and manage other conditions that can make HFrEF worse.
- Don't smoke. Smoking damages the blood vessels and raises blood pressure. It lowers blood oxygen levels and speeds up the heartbeat. Quitting can help lower the risk of heart failure getting worse. If you need help quitting, talk with your health professional. Some people with advanced heart failure may need a heart transplant. But a heart transplant may not be an option if a person keeps smoking.
- Ask about diet. People with heart failure may need to eat less salt. Salt makes the body hold onto fluid, which can make heart failure worse. A heart-healthy diet typically includes fruits and vegetables, whole grains, fat-free or low-fat dairy products, and lean proteins. It also limits saturated or trans fats. Some people with severe heart failure also may need to limit fluids.
- Ask if alcohol is safe for you. Drinking too much alcohol can weaken the heart and make heart failure worse. It also raises the risk of irregular heartbeats.
- Manage weight and stay as active as possible. Exercise can help people with HFrEF be more active and improve quality of life. But be sure to talk with your healthcare professional about an exercise program that's right for you.
Medicines
A combination of medicines may be used to treat heart failure with reduced ejection fraction (HFrEF). The specific medicines used depend on the cause of heart failure and the symptoms. Medicines recommended by heart failure guidelines are sometimes called guideline-directed medical therapy.
Medicines that have been shown to improve survival in people with heart failure with reduced ejection fraction include:
- Beta blockers. These are one of the main medicines used to treat HFrEF. They can lower the risk of hospital stays and death. Beta blockers also may be used to manage the heartbeat in people with HFrEF and atrial fibrillation (AFib).
- Angiotensin receptor plus neprilysin inhibitors (ARNIs). This medicine uses two medicines to treat HFrEF. The combination medicine is sacubitril-valsartan (Entresto). It may help prevent the need for a hospital stay in some people with HFrEF.
- Angiotensin-converting enzyme (ACE) inhibitors and angiotensin 2 receptor blockers (ARBs). These medicines may be used when an ARNI can't be used. They can lower the risk of hospital stays and death in people with HFrEF.
- Sodium-glucose cotransporter-2 (SGLT2) inhibitors. These medicines are used to treat diabetes. But research shows that this type of medicine lowers the risk of hospital stays for heart failure. It also improves survival in people with heart failure, even in those who don't have diabetes. SGLT2 inhibitors also may lower the risk of death from heart and blood vessel disease. These medicines include dapagliflozin (Farxiga) and empagliflozin (Jardiance).
- Mineralocorticoid receptor antagonists (MRAs). These medicines also are called aldosterone antagonists and work as a potassium-sparing diuretic. They include spironolactone (Aldactone, CaroSpir) and eplerenone (Inspra). These medicines may lower the risk of worsening heart failure or hospital stays in some people with HFrEF.
Unlike some other diuretics, potassium-sparing ones can raise the level of potassium in the blood to dangerous levels. Talk with your healthcare professional about your diet and potassium intake.
- Isosorbide-hydralazine (BiDil). This medicine has two medicines to treat HFrEF. In studies of Black people with HFrEF, adding BiDil to treatment helped them live longer. The medicine is not right for everyone. It only may be given if the person's blood pressure is in a certain range to take it safely.
- Positive inotropes. These medicines may be given by IV to people with advanced HFrEF. Positive inotropes can help the heart pump blood better and maintain blood pressure. They may be used for a short time in the hospital or in some people waiting for advanced heart failure treatment. Long-term use can have serious risks. Talk with your healthcare professional about the benefits and risks.
- IV iron. Some people with HFrEF have too little iron. This is called iron deficiency. If this happens, your healthcare professional may recommend iron given through a vein.
Your healthcare professional may prescribe other medicines to treat heart failure symptoms or conditions that can make it worse. These may include:
- Water pills, also called diuretics, to help remove extra fluid from your body.
- Digoxin (Lanoxin) to help control the heartbeat in some people who also have AFib.
- Statins to lower cholesterol.
- Blood thinners to prevent blood clots, which can happen with irregular heartbeats such as AFib.
- Nitrates for chest pain.
Some people with heart failure also may be told to take omega-3 fatty acid supplements. Some research shows that the supplements may help reduce the need for hospital stays.
Your healthcare professional may need to change your medicine doses frequently. This is more common when you've just started a new medicine or when your condition is getting worse.
Some heart failure medicines may lower your sex desire or cause sexual side effects. Talk with your healthcare team if you have any concerns.
Surgery or other procedures
Some people with heart failure with reduced ejection fraction (HFrEF) may need surgery or another procedure to treat the cause of heart failure or worsening heart failure.
Surgery or other procedures may include:
- Heart transplant. A heart transplant may be considered for people with advanced HFrEF that doesn't get better with other treatments.
A heart transplant isn't the right treatment for everyone. A team of healthcare professionals at a transplant center helps decide whether the procedure may be safe and beneficial for you.
- Coronary artery bypass graft (CABG) surgery. This surgery may be done if severe blockages in the heart arteries are causing or making HFrEF worse. It can improve blood flow to the heart. To do this surgery, the surgeon takes a healthy blood vessel from the leg, arm or chest and connects it from the body's main artery past the blocked arteries in the heart. The new pathway improves blood flow to the heart muscle.
- Heart valve repair or replacement. If severe heart valve disease causes heart failure, your health professional may recommend repairing or replacing the valve. There are many different types of heart valve surgery. The type needed depends on the cause of the heart valve disease. Heart valve repair or replacement may be done as open-heart or minimally invasive surgery.
Heart devices
Some people with heart failure with reduced ejection fraction (HFrEF) may need a heart device to help treat HFrEF or for advanced heart failure.
Heart devices include:
- Implantable cardioverter-defibrillator (ICD). An ICD may be used in some people with HFrEF who have a higher risk of dangerous heartbeats that can cause sudden cardiac arrest. An ICD is a device similar to a pacemaker. It's implanted under the skin in the chest with wires leading through the veins and into the heart. The ICD checks the heartbeat. If the heart starts beating at a dangerous rhythm, the ICD tries to correct the beat.
- Cardiac resynchronization therapy (CRT). Also called biventricular pacing, CRT is a treatment for heart failure in people whose lower heart chambers aren't pumping in sync with each other. A device sends electrical signals to the lower heart chambers. The signals tell the chambers to squeeze in a more coordinated way. This improves the pumping of blood out of the heart. CRT may be used with an ICD.
- Left ventricular assist device (LVAD). An LVAD helps pump blood from the left lower chamber of the heart to the rest of the body. It's also called a mechanical circulatory support device. In some people with advanced HFrEF, the device may be used while waiting for a heart transplant or as long-term treatment when a transplant isn't an option.
Cardiac rehabilitation
If you have heart failure with reduced ejection fraction (HFrEF), your health professional may suggest a supervised program of exercise and education called cardiac rehabilitation. Cardiac rehabilitation can help you safely become more active. It also may help you do daily activities more easily and improve your quality of life.
Symptom care and end-of-life care
If you have heart failure with reduced ejection fraction (HFrEF), your healthcare professional may recommend special medical care to reduce symptoms and improve quality of life. This is called palliative care. Palliative care can be given at any stage of heart failure. It can help with symptoms and support you and your family.
In some people with heart failure, medicines no longer work and a heart transplant or device isn't an option. If this occurs, special end-of-life care may be recommended. This is called hospice care. Hospice care is for people nearing the end of life when treatments to prolong life are no longer the main focus.
Hospice care allows family and friends — with the aid of nurses, social workers and trained volunteers — to care for and comfort a loved one. Hospice care is available in your home or in nursing homes and assisted living centers. It provides emotional, psychological and spiritual support for those who are sick and their loved ones.
Prognosis
Prognosis means what may happen over time. It is an estimate of what will happen. But it doesn't say what exactly will happen. It also means how well you may do after treatment. Heart failure with reduced ejection fraction (HFrEF) is a serious, long-term condition. How well a person with heart failure does varies widely. It is different for each person. It depends on age, symptoms and other health conditions.
There is no single life expectancy that applies to everyone with HFrEF. Treatment can improve symptoms and lower the risk of some hospital stays.
Más información
Estudios clínicos
Explora los estudios de Mayo Clinic que ensayan nuevos tratamientos, intervenciones y pruebas para prevenir, detectar, tratar o controlar esta afección.
Self-care
You can take an active part in your care. Follow the treatment plan that your healthcare team gives you for heart failure with reduced ejection fraction (HFrEF). Your care team may ask you to:
- Check your legs, ankles and feet for swelling. Do this every day. Call your healthcare professional if the swelling gets worse.
- Weigh yourself every day. Weight gain may mean your body is holding onto fluid. You may need a change in treatment. Call your health professional if you gain 5 pounds (2.3 kilograms) or more within a few days.
- Ask about salt and fluid intake. If you have severe heart failure, your health professional may suggest that you limit fluids. Anything that melts into a liquid counts toward your daily fluid limit. These things include ice, soup, ice cream and juicy fruits. Also ask your health professional if you need to follow a no-salt or low-salt diet. Too much salt, also called sodium, can make the body hold onto water. This is called water retention. It makes the heart work harder.
- Take medicines as directed. If side effects or costs are a concern, ask your health professional about options. Don't stop taking your medicines without talking to a health professional.
- Use caution with medicines and supplements. Some medicines that you can get without a prescription to treat pain and swelling can make heart failure worse. They include ibuprofen (Advil, Motrin IB, others) and naproxen sodium (Aleve). Some diet pills and supplements also may be unsafe if you take medicines for heart failure. Always tell your healthcare professional about all the medicines you take, including those bought without a prescription.
- Get recommended vaccinations. Ask your healthcare professional about getting influenza, pneumonia and COVID-19 vaccinations.
Heart failure action plan
Heart doctors recommend that all people with heart failure have an action plan to help guide their self-care at home. A heart failure action plan, also called a self-check plan, provides clear instructions for you and your caregivers to follow should any new symptoms develop. You can work with your healthcare team to create a plan based on your needs and type of heart failure.
According to the American Heart Association, a typical plan can fall into three zones:
- Green = Stable. You don't have noticeable changes in heart failure symptoms. Your weight is stable. You don't have chest pain or shortness of breath. Continue your daily weight checks and treatment plan as recommended.
- Amber = Warning. Call your healthcare team if you have a new cough, shortness of breath with activity, increased swelling in your legs or feet, or if you suddenly gain 2 to 3 pounds (about 1 to 1.5 kilograms) overnight or 5 pounds (just over 2 kilograms) in a week. You might not need an office visit. But you might need to change your diet or medicines. Follow the instructions in your plan.
- Red = Danger. Go to the emergency room or call your local emergency number if you have heart failure and have gained more than 5 pounds (just over 2 kilograms) in a week. Also seek help if you can't lie flat, are short of breath at rest, have increased swelling and discomfort in the lower body, or have a constant, hacking cough.
Strictly following your action plan can help your healthcare professional quickly treat new health issues that develop and manage your care.
Estrategias de afrontamiento y apoyo
If you have heart failure with reduced ejection fraction (HFrEF), it's important to manage emotional stress. Stress, anxiety and other strong emotions can affect your heart and may make heart failure symptoms feel worse.
Practicing methods such as mindfulness may help. Some people also find that talking about their concerns with others in similar situations can help. You might try to connect with friends or family or join a support group.
Counseling
Heart failure and some heart failure medicines can affect sexual activity and sexual desire. The American Heart Association and the European Society of Cardiology suggest sexual counseling for people with heart disease and their partners. This includes people with heart failure with reduced ejection fraction (HFrEF).
Sex is a form of exercise. If you have heart failure and exercise makes you feel winded, you might wonder if it is safe to have sex. Sexual activity may not be safe if you have advanced heart failure or heart failure that's not stable. Also some heart failure medicines may lower your desire for sex or cause sexual side effects.
Sexual counseling can help answer questions and build confidence and closeness. It also can give useful tips on how to have sex again safely. If your heart failure is stable, sexual activity may be safe. If it is not safe yet, kissing and touching may still be OK. Finding ways to stay sexually active can support your quality of life and help you stay close to your partner.
If you have concerns about heart failure and sex, talk with your healthcare team about your concerns.
Preparación para la consulta
If you have symptoms of heart failure with reduced ejection fraction (HFrEF) or are worried about your risk, make an appointment with your healthcare professional. You may be sent to a doctor who is trained in heart diseases. This type of doctor is called a cardiologist. Finding heart failure early can help you get the right treatment sooner.
Appointments can be brief. Because there's often a lot to discuss, it's a good idea to be prepared for your appointment. Here's some information to help you get ready.
What you can do
- Ask if there's anything you need to do in advance. For example, you may be told not to eat or drink for a while before some tests.
- Write down your symptoms. Include any that may not seem related to heart failure with reduced ejection fraction (HFrEF).
- Write down important personal information. Include any family history of heart disease, stroke, high blood pressure or diabetes. Find out if anyone in your family has had heart failure. Some heart conditions that cause heart failure run in families. Knowing as much as you can about your family history can be helpful. Also note any major stresses or recent life changes.
- Make a list of all medicines, vitamins or supplements that you're taking. Include doses. Bring this list with you to all health checkups.
- Take someone along if possible. Sometimes it can be hard to remember all the information given to you during an appointment. Someone who goes with you may remember something that you missed or forgot.
Your time with your healthcare professional is limited. Preparing a list of questions can help you make the most of your time together. List your questions from most important to least important in case time runs out. For heart failure with reduced ejection fraction (HFrEF), some basic questions to ask your healthcare professional include:
- What's the most likely cause of my symptoms?
- Are there other possible causes for my symptoms?
- What kinds of tests do I need? Do I need to do anything to get ready for them?
- What is my ejection fraction, and has it changed?
- What treatments are available? Which do you recommend for me?
- How will we know if my treatment is working?
- What symptoms or weight changes should I call you about?
- How often do I need checkups or tests for my HFrEF?
Also ask these questions:
- I have other health conditions. How should I manage them along with my HFrEF?
- Do I need to limit salt, fluids or any foods? If so, what are my restrictions?
- Do I need to change my activities?
- Is it safe to have sex?
- Should my family members be checked for heart conditions that can run in families?
- Is there information I can take home? What websites do you recommend?
Don't hesitate to ask other questions.
What to expect from your doctor
Your healthcare professional is likely to ask many questions. Being ready to answer them may save time to go over any details you want to spend more time on. Your healthcare professional may ask:
- When did you first notice your symptoms?
- Do your symptoms occur all the time, or do they come and go?
- How severe are your symptoms?
- Do you get short of breath with activity or when lying flat?
- Have you been less active because of your symptoms?
- Have you noticed swelling in your legs, ankles, feet or belly?
- Have you gained weight quickly?
- What, if anything, seems to improve your symptoms?
- Does anything make your symptoms worse?
- What medicines and supplements do you take?
Sept. 26, 2026