Diagnosis
Transthyretin amyloid cardiomyopathy (ATTR-CM) can be challenging to diagnose. Its early symptoms can be a lot like those of other more common heart conditions. Talk about all your symptoms with your healthcare professional. Doing so may help with the diagnosis. For example, a history of carpal tunnel syndrome, especially in both hands, spinal stenosis, tendon rupture or nerve symptoms that are not explained can help your care team recognize ATTR-CM.
To diagnose ATTR-CM, a healthcare professional asks about your symptoms, your health history and your family health history. Next, your healthcare professional examines you and listens to your heart.
You also may need tests to check your heart and look for causes of your symptoms.
Electrocardiogram (ECG/EKG)
Transthyretin amyloid cardiomyopathy (ATTR-CM) can cause changes in the electrical signals that make the heart beat.
An ECG shows how the heartbeat signals move through your heart. The test is quick and painless. An ECG can often be done when you first see your healthcare professional. The test can find irregular heartbeats, heart block and other changes that may give clues to ATTR-CM.
To do the test, sticky patches with sensors on them go on your chest and sometimes your arms and legs. Wires connect the sensors to a computer, which prints or shows the results.
Electrocardiogram
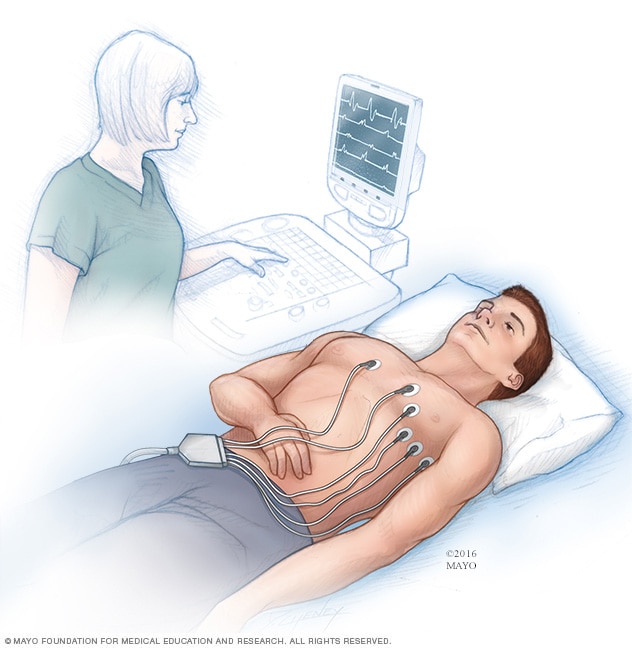
Electrocardiogram
An electrocardiogram (ECG or EKG) is a test to record the electrical signals in the heart. It shows how the heart is beating. Sticky patches called electrodes are placed on the chest and sometimes on the arms or legs. Wires connect the patches to a computer, which prints or displays results.
Blood and urine tests
Some blood and urine tests can help find signs of cardiac amyloidosis such as transthyretin amyloid cardiomyopathy (ATTR-CM). Results from some of the tests help your care team learn how much damage there is to the heart and other organs. But these tests can't diagnose ATTR-CM by themselves.
Blood tests may include:
- Troponin. This is a protein found in heart muscle. Higher levels of the protein in the blood may mean more heart muscle damage.
- N-terminal pro-B-type natriuretic peptide (NT-proBNP). The heart releases this substance into the bloodstream when it's under increased strain or pressure. High levels may be a sign that amyloidosis has affected the heart. Changes in the NT-proBNP level also help show how treatment is working. If NT-proBNP testing is not available, your healthcare professional may do a regular BNP test.
- Estimated glomerular filtration rate (eGFR). This blood test shows how well the kidneys are working. It checks the level of a waste product called creatinine that's made by muscles. Then it estimates how much blood the kidneys filter each minute. In cardiac amyloidosis, the eGFR may go down if the kidneys are not doing their job well.
- Other blood tests. ATTR-CM can affect more than the heart. Other blood tests may be done to see how well other parts of the body are working.
Other blood and urine tests may be done to rule out another type of cardiac amyloidosis called amyloid light-chain (AL) amyloidosis. These tests include:
- Immunoglobulin free light chains. This blood test measures two small protein pieces called kappa and lambda free light chains. It also checks whether there is more of one type than the other. A higher level of one type or a change in the balance between the two may be a sign of AL amyloidosis. Kidney disease also can affect free light chain levels. That means your care team needs to look at the results with care.
- Electrophoresis and immunofixation. These tests check blood and urine for a protein called a monoclonal protein (M protein). Finding a monoclonal protein may suggest AL amyloidosis. But some people with ATTR also can have an unrelated monoclonal protein. So more testing, including at times a biopsy, is needed to confirm the type of amyloidosis. Your healthcare professional considers the test results with those from the free light chain test.
Imaging tests
Imaging tests for transthyretin amyloid cardiomyopathy (ATTR-CM) make pictures of the heart. They can show changes caused by amyloid buildup. Imaging tests to help diagnose or monitor the condition may include:
- Chest X-ray. A chest X-ray shows the condition of the lungs and heart. It can show whether the heart is larger than usual. But a chest X-ray can't diagnose ATTR-CM.
- Echocardiogram. This usually is one of the first imaging tests done to help diagnose cardiac amyloidosis, including ATTR-CM. Sound waves make moving pictures of the beating heart. The test shows the thickness of the heart walls and how well the heart fills, relaxes and pumps blood. It also can show patterns in the heart that suggest amyloid buildup. But the test can't tell the type of amyloid.
- Heart MRI, also called cardiac MRI. This test uses radio waves and a strong magnetic field to make clear pictures of the heart tissue. It shows the structure of the heart. It also can show patterns related to amyloid buildup. This test may be done when more information about the heart is needed.
- Single-photon emission computerized tomography scan (SPECT scan). This is a type of nuclear imaging. It's the main nuclear imaging test used to find ATTR cardiac amyloidosis. The test uses a small amount of a radioactive substance called a tracer. If a lot of the tracer collects in the heart during this test and blood and urine tests do not show signs of AL amyloidosis, ATTR-CM may be diagnosed without a heart biopsy.
- Amyloid positron emission tomography scan (PET scan). This is another nuclear imaging test. It uses a small amount of a tracer that's made to stick to amyloid. Amyloid PET scans are being studied as another way to find and measure amyloid in the heart. But PET scans for ATTR-CM are still investigational. They are not part of routine diagnosis. The test is generally available only at specialized centers or through research studies.
Echocardiogram
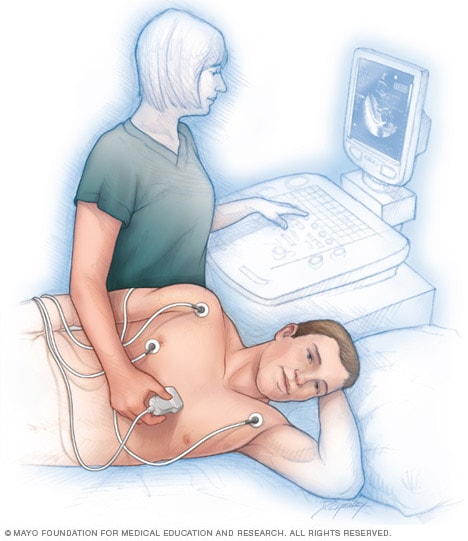
Echocardiogram
An echocardiogram uses sound waves to show how blood flows through the heart and heart valves. Sensors also may be attached to the chest and sometimes the legs to check the heartbeat during the test. The test can help a healthcare professional diagnose some heart conditions.
Heart biopsy
Your healthcare professional may suggest a heart biopsy when other tests for transthyretin amyloid cardiomyopathy (ATTR-CM) don't give a clear answer.
A heart biopsy is the removal of a piece of heart tissue to be checked under a microscope. The test is usually done in a hospital. A doctor places a thin, flexible tube, called a catheter, through a blood vessel and guides it into the heart. A tiny tool at the end of the tube removes a few small pieces of heart tissue. The tissue goes to a lab where it's checked for amyloid and the type of amyloid.
Your care team uses the results of all tests to diagnose ATTR-CM and plan your care.
Genetic testing
Some types of cardiac amyloidosis can be passed down through families. If you have transthyretin amyloid cardiomyopathy (ATTR-CM), your healthcare professional may suggest genetic testing. Such testing can show whether you have the wild type or hereditary type. Imaging tests can't tell these two types apart.
Genetic testing is important even if no one in your family is known to have ATTR-CM. The test can determine whether the ATTR-CM is hereditary or wild-type. Many people with a change in the gene for transthyretin do not know of anyone else in their family who has ATTR-CM. Some relatives with the gene change may never develop symptoms. Others may develop symptoms later in life or may have the condition without being diagnosed. If you have hereditary ATTR, your healthcare professional may recommend that your parents, siblings and children also be checked.
Ask your healthcare professional if genetic testing is right for you. A genetic counselor can explain what the result may mean for you and your family.
Care team
If testing shows that you have transthyretin amyloid cardiomyopathy (ATTR-CM), different healthcare professionals work together to treat your condition and support your care. You do not have to manage the condition on your own.
Your specific care team depends on your individual needs. The team may include:
- Doctors trained in heart disease, called cardiologists.
- Other heart specialists who care for and treat irregular heartbeats and heart failure.
- Doctors trained in nerve conditions, called neurologists.
- Genetic counselors.
- A primary care healthcare professional.
More Information
Treatment
There's no single treatment that cures transthyretin amyloid cardiomyopathy (ATTR-CM) or reverses all the damage in the heart. But newer treatments can help slow or stop more amyloid from forming. Treatments also can help prevent further damage.
Your healthcare team works with you to create an ATTR-CM treatment plan that fits your condition and symptoms. The goals of treatment are to:
- Manage symptoms.
- Keep the condition from getting worse.
- Lower the risk of complications.
Treatment includes medicines that target the cause of amyloidosis. It also includes medicines that help the heart work better. The type of medicine you need may change over time.
Your healthcare team may change your treatment based on:
- How much your heart is affected.
- Whether other organs are affected.
- Your overall health.
Medicines for ATTR-CM
There are two main types of medicines used to treat transthyretin amyloid cardiomyopathy (ATTR-CM).
- TTR stabilizers. These medicines help stop the transthyretin (TTR) protein from breaking apart. This slows amyloid from forming. But they do not remove amyloid already in the body. TTR stabilizers used to treat transthyretin amyloid cardiomyopathy include tafamidis (Vyndamax) and acoramidis (Attruby). By slowing the disease, these medicines can help people stay active longer. The medicines may help protect quality of life. They also can lower the risk of death and hospital stays for heart concerns. TTR stabilizers may affect some thyroid hormone blood tests, usually without causing thyroid disease. Side effects vary by medicine. Acoramidis may cause diarrhea and stomach pain. Tafamidis is generally well tolerated.
-
TTR silencers. These medicines lower the amount of transthyretin protein made by the liver. Vutrisiran (Amvuttra) is one example. Research shows that vutrisiran helps people with wild-type or hereditary ATTR-CM live longer. It also lowers the chance of hospital stays for heart-related reasons. The medicine also treats nerve damage due to polyneuropathy of hereditary transthyretin-mediated amyloidosis.
Vutrisiran is given as a shot under the skin. Side effects may include pain in the arms or legs, joint pain, shortness of breath, and low vitamin A. People taking vutrisiran need vitamin A supplements. Follow the advice of your healthcare team.
If a medicine is not a good fit or the condition continues to get worse, your care team may consider other treatment options. A clinical trial also may be an option.
Medicines to treat symptoms and prevent complications
Your healthcare professional also may give you medicines to treat your symptoms and to prevent complications. Medicines can help:
- Control irregular heartbeats.
- Remove extra fluid from the body.
- Prevent blood clots.
Some medicines commonly used for heart failure or high blood pressure may not work well for people with transthyretin amyloid cardiomyopathy (ATTR-CM). They also may cause blood pressure to drop too low. Your healthcare team chooses these medicines carefully.
Heart transplant
If amyloid deposits cause a lot of damage to your heart, you might need a heart transplant. During a heart transplant, a surgeon removes your heart and replaces it with a donor heart. A heart transplant may be a treatment option for some people with advanced ATTR-related heart failure.
Cardiac ablation
If ATTR-CM causes an irregular heartbeat called AFib, some people may need a treatment called atrial fibrillation cardiac ablation. Most often, a doctor places one or more thin, flexible tubes called catheters into a blood vessel and guides them to the heart. The doctor then uses heat or cold energy to create small scars in the heart. The scars block the faulty heart signals that cause AFib.
AFib can come back after ablation, particularly in people with more advanced ATTR-CM. You and your healthcare team can decide whether ablation is right for you.
Heart devices
Some people with transthyretin amyloid cardiomyopathy (ATTR-CM) have a very slow heartbeat or other dangerous heartbeat changes. They may need a heart device to control the heartbeat or help the heart pump more effectively. The device is placed under the skin of the chest during minor surgery. Heart devices may include:
- Pacemaker. If ATTR-CM makes your heart beat too slowly, you may need this device. It helps keep the heart beating regularly.
- Implantable cardioverter-defibrillator (ICD). This device is a treatment for certain dangerous heartbeats. It delivers an electric shock when needed to restore a regular heartbeat. ICDs are not routinely used for everyone with ATTR-CM.
- Cardiac resynchronization device. This is a treatment for some people with moderate to severe heart failure. It helps the heart chambers squeeze in a better and more organized way.
After treatment for ATTR-CM, you need regular health checkups. This may include tests to check your heart and to see how well treatment is working.
Prognosis
Prognosis means what may happen with the condition over time. It also means how well you may do after treatment. It also may be called your outlook.
The prognosis for transthyretin amyloid cardiomyopathy (ATTR-CM) differs for each person. No single life-expectancy estimate applies to everyone treated today. The condition can be life-threatening. But newer treatments can slow the condition and help people live longer.
The prognosis depends on:
- The type of ATTR.
- The stage of ATTR-CM when it is diagnosed.
- How well your heart and kidneys work.
- Your age.
- Overall health and whether you have other medical conditions.
People who have milder symptoms and start treatment before severe heart damage happens tend to have a better prognosis.
For hereditary ATTR amyloidosis, the specific change in the TTR gene may affect when your symptoms start. It also may affect which organs are involved and how your condition changes over time. Your healthcare professional may suggest genetic counseling. A genetic counselor can explain what your gene change may mean for you and your family.
To understand your prognosis, your healthcare team uses results from blood tests and imaging tests, such as echocardiograms and cardiac MRI. No single test can predict exactly what will happen to one person.
More Information
Clinical trials
Explore Mayo Clinic studies testing new treatments, interventions and tests as a means to prevent, detect, treat or manage this condition.
Lifestyle and home remedies
Transthyretin amyloid cardiomyopathy (ATTR-CM) can make everyday activities harder because you may feel tired, weak or short of breath. These steps may help you manage symptoms and stay as active as you can.
- Take your medicines as directed.
- Go to your regular health checkups.
- Do not smoke.
- Follow your healthcare team's advice about salt and fluids.
- Talk to your care team before you make major changes to your diet or activities.
- Stay active in ways your healthcare team says are safe.
- Rest when you feel tired.
It also is important to manage emotional stress. Learning that you have ATTR-CM may be hard. Some people find that talking about their concerns with others in similar situations can help. You might connect with friends or family or join a support group.
Preparing for your appointment
If you have symptoms of transthyretin amyloid cardiomyopathy (ATTR-CM) or are worried about your risk of the condition, make an appointment with your healthcare professional. You may be sent to a doctor trained in heart disease, called a cardiologist.
Appointments can be brief. Because there's often a lot to talk about, it's a good idea to be prepared for your appointment. Here's some information to help you get ready.
What you can do
When you make your appointment, ask if you need to do anything in advance. For example, you may be told not to eat or drink for a while before some tests.
Other things you can do to prepare:
- Write down any symptoms. Include those that may not seem related to transthyretin amyloid cardiomyopathy (ATTR-CM).
- Write down important personal information. Tell your healthcare team if you have a family history of ATTR amyloidosis. Knowing as much as you can about your family history can help your care team make a diagnosis.
- Make a list of all the medicines, vitamins and supplements that you take. Include the doses.
- If possible, ask someone to go with you to help you remember what your care team says.
Also write down questions to ask your healthcare team. For ATTR-CM, some basic questions include:
- What organs are affected?
- What tests do I need?
- What treatments do I need?
- What types of side effects can I expect from treatment?
- What are the possible complications?
- Do I need to change my diet or activities?
- Should I consider genetic testing or genetic counseling?
Don't hesitate to ask other questions during your appointment.
What to expect from your doctor
Your healthcare team usually asks many questions, such as:
- When did your symptoms start?
- How bad are they?
- Do the symptoms come and go, or do you have them all the time?
- Does anything make your symptoms better or worse?
- How is your appetite?
- Have you recently lost weight without trying?
- Have you had any swelling in your legs, feet or ankles?
- Have you felt short of breath?
- Are you able to work and do your usual daily tasks?
- Has anyone in your family ever been diagnosed with amyloidosis?
Sept. 15, 2026